Interactive Decision Support
Differential Diagnosis Trees
Work through common presentations step-by-step with interactive decision trees. Click through questions to narrow your differential.
Acute Dyspnea
See the whole tree (5 outcomes)
- Does the patient have fever?
- Yes - Fever present (Temperature > 38°C)
- Any productive cough or sputum?
- Yes - Productive cough
- 🫁 Consider Pneumonia / AECOPD: Check CXR for infiltrate. Send sputum culture. Start antibiotics if suspicion high. Consider AECOPD if known COPD. → See Sepsis Protocol and AECOPD Protocol
- No - Dry cough or no cough
- 💔 Consider PE, Viral Pneumonitis, or Sepsis: Check D-dimer and consider CTPA if PE suspected. Look for other source of infection. → See Sepsis Bundle
- Yes - Productive cough
- Any productive cough or sputum?
- No - No fever (Afebrile presentation)
- Is there chest pain or pressure?
- Yes - Chest pain present
- 💔 Consider ACS, PE, or Pneumothorax: Get ECG immediately. Check troponin. Consider CTPA for PE. CXR for pneumothorax. → Start ACS workup
- No - No chest pain
- Any leg swelling or immobilization?
- Yes - DVT risk factors
- 🩸 PE likely - start workup: Check Wells Score. D-dimer if low/moderate risk. CTPA if high risk or positive D-dimer. → See PE Protocol
- No - Chronic dyspnea
- 💔 Consider Heart Failure, COPD, or Anemia: Check BNP, echo, PFTs. Review medications. CXR for cardiomegaly/edema. → See Heart Failure or AECOPD
- Yes - DVT risk factors
- Any leg swelling or immobilization?
- Yes - Chest pain present
- Is there chest pain or pressure?
- Yes - Fever present (Temperature > 38°C)
Chest Pain
See the whole tree (4 outcomes)
- Is the pain sharp and positional?
- Yes - Sharp, positional (Worse with breathing or movement)
- Any recent trauma or cough?
- Yes - Recent trauma/cough
- 🦴 Consider Musculoskeletal or Rib Fracture: Tenderness to palpation suggests MSK. CXR if concerned for fracture. Rule out pneumothorax.
- No - No trauma
- 🫁 Consider Pericarditis, Pleuritis, or PE: ECG for PR depression. Check troponin. Friction rub? Consider CTPA for PE. → See Pericarditis workup
- Yes - Recent trauma/cough
- Any recent trauma or cough?
- No - Pressure/squeezing (Substernal pressure)
- Any cardiac risk factors? (DM, HTN, smoking, age > 50)
- Yes - Risk factors present
- 🚨 ACS until proven otherwise: Get ECG within 10 min. Serial troponins. Aspirin 325mg. Cardiology consult. → Start STEMI/NSTEMI Protocol
- No - Low cardiac risk
- 🫀 Still check troponin and ECG: Young patients can still have ACS. Consider PE, aortic dissection, esophageal spasm. → Full cardiac workup
- Yes - Risk factors present
- Any cardiac risk factors? (DM, HTN, smoking, age > 50)
- Yes - Sharp, positional (Worse with breathing or movement)
Altered Mental Status
See the whole tree (4 outcomes)
- Is glucose normal? (Check immediately)
- Low glucose < 70
- 🍬 Hypoglycemia - Treat NOW: Give D50 1 amp IV or glucagon 1mg IM. Recheck q15min. Find cause: insulin, sepsis, liver failure, adrenal insufficiency.
- Normal glucose
- Any fever or signs of infection?
- Yes - Fever/infection present
- 🦠 Consider Sepsis, Meningitis, Encephalitis: LP if no contraindications. Blood cultures x2. Start empiric antibiotics. Head CT before LP if focal deficits. → Sepsis Bundle
- No - No fever
- Any focal neurological deficits?
- Yes - Focal deficits
- 🧠 STROKE - activate code stroke: Get STAT head CT. Check last known normal. Consider tPA if < 4.5hrs. → Stroke Protocol
- No - Diffuse confusion
- 🧪 Check metabolic causes: NH3 (hepatic enceph), TSH (hypothyroid), toxicology screen, check meds (benzos, opioids). Uremia? → Metabolic workup
- Yes - Focal deficits
- Any focal neurological deficits?
- Yes - Fever/infection present
- Any fever or signs of infection?
- Low glucose < 70
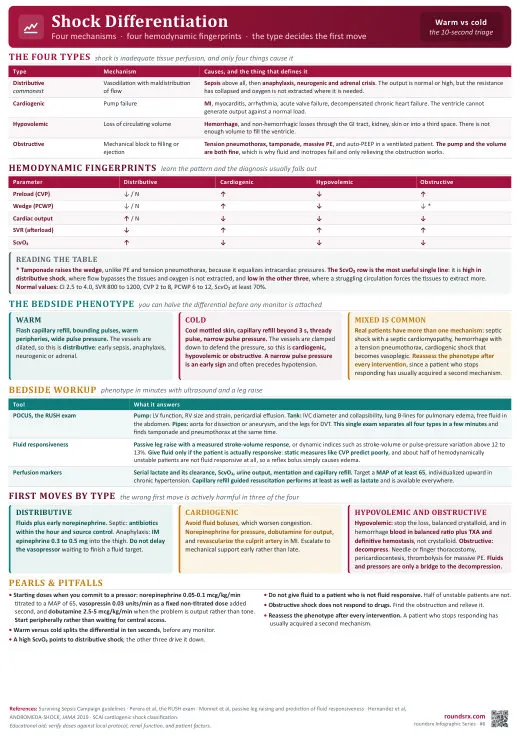
Hypotension / Shock
See the whole tree (4 outcomes)
- Is the patient warm or cold?
- Warm extremities (Warm, bounding pulses)
- Any signs of infection?
- Yes - Infection likely
- 🦠 Distributive Shock (Sepsis): Start 1-hour sepsis bundle: cultures, antibiotics, 30mL/kg fluids, lactate. Norepinephrine if MAP < 65. → Sepsis Protocol
- No - No clear infection
- ⚠️ Anaphylaxis, Neurogenic, or Adrenal Crisis: Epinephrine if anaphylaxis. Hydrocortisone if adrenal crisis. Check history for spinal injury (neurogenic).
- Yes - Infection likely
- Any signs of infection?
- Cold extremities (Cool, mottled skin)
- Are neck veins distended (JVD)?
- Yes - JVD present
- 💔 Cardiogenic or Obstructive Shock: Echo STAT. Look for tamponade, PE, tension PTX. Inotropes if cardiogenic. → Cardiogenic Shock Protocol
- No - Flat neck veins
- 🩸 Hypovolemic Shock: Fluid resuscitate 1-2L bolus. Look for bleeding (GI, AAA, trauma). Transfuse if Hgb < 7. → Find source and stop bleeding
- Yes - JVD present
- Are neck veins distended (JVD)?
- Warm extremities (Warm, bounding pulses)